One of the most confusing things for students entering Clinical Behavior Analysis is that psychologists often seem to disagree about almost everything.
They disagree about diagnoses. They disagree about treatment. They disagree about what should be measured. They even disagree about what counts as good evidence.
It is tempting to think these disagreements arise because people simply have different opinions. More often, however, they begin much earlier. They begin with different assumptions about what science is trying to accomplish.
Steven Hayes described these assumptions in Varieties of Scientific Contextualism (1992), drawing on the work of philosopher Stephen Pepper. Before we can understand why behavior analysts think differently about measurement, treatment, or theory, it helps to understand the philosophical ground on which those decisions are made.
Hayes argues that philosophies of science can be understood as different “world hypotheses.” Each begins with a root metaphor—a basic way of understanding how the world works. That metaphor influences what questions become important, what counts as evidence, and ultimately how scientists decide whether they are making progress.
Although there are many philosophical positions, four have been particularly influential in psychology.
The oldest approach is formism. Its root metaphor is similarity or form. The world is understood by identifying things that belong together and giving them names. The scientific task becomes classification. This approach gave us taxonomies, categories, and much of our early scientific thinking. In psychology, it is reflected whenever we ask, “What disorder does this person have?” or “Which category does this behavior belong in?”
Naming is useful. But naming is not the same thing as understanding. Two people may both receive a diagnosis of major depressive disorder while behaving very differently and responding to entirely different interventions. Formism helps us organize observations. It does not necessarily explain why they occur.
Mechanism extends formism. Its metaphor is the machine. If we understand the parts and how they interact, we can explain the system. Truth becomes a matter of correspondence. Our theories are considered better to the extent that they accurately represent how reality actually works. Much of modern medicine follows this approach. Find the broken mechanism. Repair it. Psychology has inherited many mechanistic assumptions as well. We often search for underlying mechanisms, latent variables, or internal systems presumed to generate behavior. Mechanistic methods have produced tremendous advances. Hayes is careful to point out that functional contextualists borrow many of these methods. The danger is not the methods themselves.
The danger is quietly adopting the assumptions that accompany them.
Organicism begins with a different metaphor. The world is viewed as an unfolding story. Events that appear contradictory today may eventually make sense when viewed within a larger developmental narrative. Truth is evaluated by coherence. Does this explanation fit within the broader story? Developmental psychology often leans in this direction. Individual events become meaningful because of the role they play within an evolving system. Again, this perspective offers valuable insights. But it answers a different kind of question.
Contextualism asks a different question altogether. Its root metaphor is the act-in-context. Rather than asking what something is, contextualism asks what it does, under what conditions it occurs, and what difference that understanding allows us to make. The truth criterion becomes successful working, or what Hayes calls workability. Importantly, something can only “work” relative to a stated goal. If our goal is to reduce panic attacks, improve relationships, increase adherence to medical treatment, or help someone live more consistently with their values, then our scientific models are judged by whether they help us move toward those outcomes.
William James is generally considered the father of contextualism; however, Skinner’s work reflected an implicit contextualist philosophy long before these distinctions were discussed explicitly.
Hayes makes an important distinction between two forms of contextualism.
Descriptive contextualism attempts to appreciate the richness of the whole. The goal is understanding. James, Dewey, and Kantor each worked largely within this tradition. Here, coherence remains important because the scientist is attempting to capture the complexity of an event as completely as possible.
Functional contextualism asks a different question. Can this analysis improve our ability to predict and influence behavior? The goal is practical rather than descriptive. Hayes compares this to engineering. Knowing that a bridge will collapse is useful. Knowing how to build one that won’t collapse is far more useful. That shift has enormous implications for psychology.
A functional contextualist is less interested in whether a theory is elegant than whether it increases our ability to predict and influence behavior toward meaningful goals.
This philosophical foundation explains why Clinical Behavior Analysis often approaches familiar problems differently than other traditions. When behavior analysts question diagnoses, latent constructs, or statistical summaries, they are not necessarily rejecting them outright.
They are asking a different question.
What additional predictive or practical value does this way of describing behavior provide?
Sometimes the answer is “quite a lot.” Sometimes the answer is “not much.” That becomes an empirical question rather than a philosophical argument. This perspective also explains why measurement has become such an important issue for our field.
If our goal is to predict and influence behavior, then the quality of our measurement becomes central. As our technologies improve, we are no longer limited to occasional questionnaires or broad diagnostic categories. We can increasingly observe behavior unfolding across time, context, physiology, language, and daily life.
That doesn’t mean our older methods were mistakes. They represented the best measurements we had available. But science progresses by improving observation. Clinical Behavior Analysis, at its best, has always been about improving our ability to understand behavior in context.
Referecnces
Hayes, S. C. (1993). Varieties of Scientific Contextualism. Reno, NV: Context Press.
Pepper, S. C. (1942). World Hypotheses: A Study in Evidence. University of California Press.

Clinical Behavior Analyst, Methodologist & Trainer
Angela J. Coreil, PhD, is a professor at the University of Louisiana at Lafayette, clinical behavior analyst, and methodologist. Formerly director of an OCD and anxiety IOP/PHP, she integrates behavior analysis, ACT, Interpersonal Behavior Therapy, CBT, and exposure-based treatment. Her work develops practical improvements in behavioral science, and she provides consultation, professional training, workshops, and continuing education across disciplines.
Views expressed are those of Dr. Coreil or the explicitly named author, not the University of Louisiana at Lafayette.

This may be a time of transition for psychology. Our path as a field has led to some great advances, but as it has grown, it appears to have come undone at the seams.
The need for a standard metric.
As clinicians, we struggle to gain reimbursement and prove our effectiveness in meaningful terms to our clients. As researchers and academics, we are now at a point of crisis such that the NIH has begun a funding initiative demanding coherent metrics from our field.
If we are to remain a credible and effective science, we must do it not by arguing for small islands of theoretical turf but by deep integration and coherence in our methods. From there, we can build a solid base on which to help humanity tackle its largest issues.
Measuring dynamic relationships between behavior and context is the place to begin.
Starting with a more basic level of observations in measurement allows us to realign on solid ground. Our field departed from this with traditional CBT, which led to a great deal of gains. And we must be clear about that – it would be easy to ‘poo poo’ this progress now; however, we need to be careful not to invalidate our own foundation and history.
Let RFT stand larger than ACT.
We moved to measuring constructs like “psychological flexibility,” “self-confidence, ” “anxiety sensitivity” because we did not have a way to measure and understand the complexity of behaviors humans constantly. Look around now: where is your iPhone? Where is your Fitbit? Where is your Alexa? Is your browser open? Guess what. Consumer goods are currently measuring intensive flows of your behavioral data right now. Sadly, psychology and behavior analysis haven’t caught up to the fact that we no longer need to rely on the most rudimentary of measurements.
Consultant and Educator
Angela J. Coreil, PhD works with individuals and organizations to promote better connected, purposeful, and effective living through behavior analytic principles. She has over a decade of clinical experience treating human suffering and promoting human excellence using Acceptance and Commitment Therapy (ACT) and other behavioral therapies. She now focuses on the promotion and translation of Clinical Behavior Analysis as a way to improve our science.
Editor’s Note (2026): This article was originally published on AngelaCathey.com in 2016. It is reproduced here with only minor grammatical edits for readability. Some resources and terminology have evolved since its original publication, but the conceptual discussion is presented largely as it appeared at that time.
UNDERSTANDING PROPERTIES OF RFT: The signal in noise of human behavior
Now that we’ve talked about space-time distortion, let’s blow your mind a bit more by learning to understand the properties of RFT.
You’ve all seen the diagrams explaining how the letters in the word “cat” = a picture of a cat = the sound of “cat” spoken. You may have also seen the complex ‘algebra’ that formulaically explains properties of RFT like transformation of stimulus function.
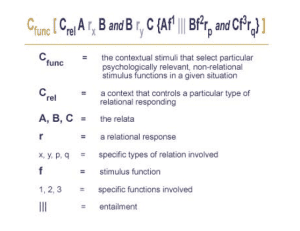
See: https://contextualscience.org/transformation_of_stimulus_functions
Yikes! So, that formula is sheer genius but not particularly functional for people who don’t already understand RFT. Explaining RFT in these terms to those who are learning is a bit like explaining gravity as a formula. In some way it is ‘true,’ but if you want someone to understand the meaning of gravity, you’re better off dropping the DSM on their foot.
Let’s understand the meaning of RFT at a deeper, more experiential level.
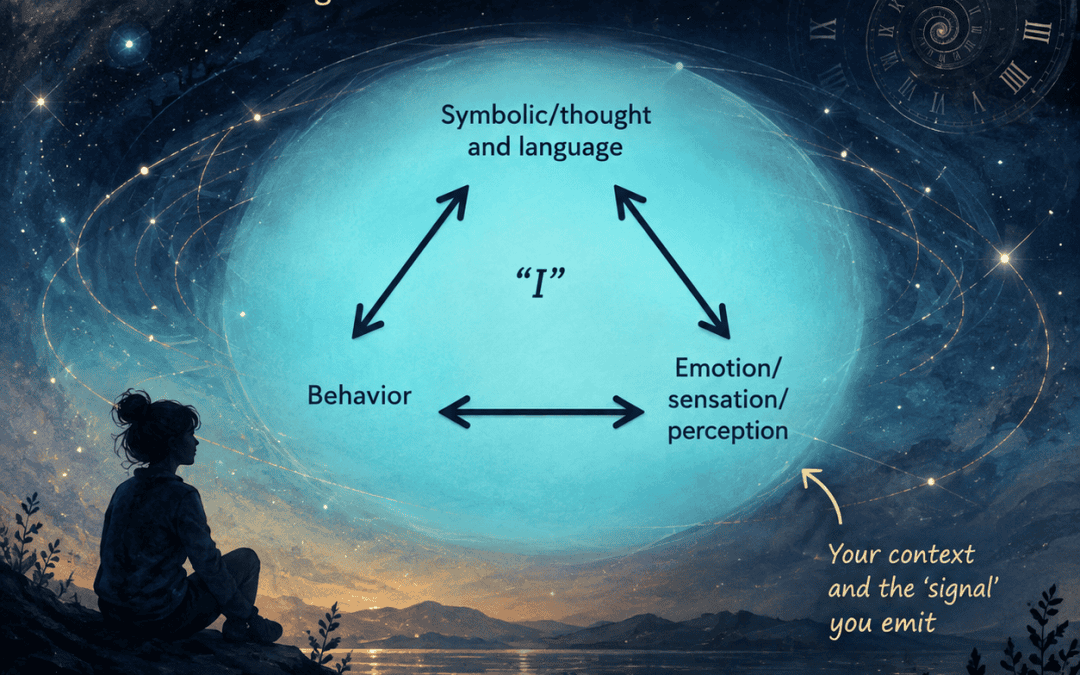
RFT explains the inter-relations of different elements of our behavior and context.
 Diagram: Cathey (2016)
This is a diagram showing how the properties of RFT and operant/classical conditioning tell us that our behaviors are interrelated.
It’s not perfect. Anyone can tell you these aren’t entirely separate.
Our experience is actually much more like this.

Picture: indulgy.com
Let’s dig a little deeper…

So, in some way we are this relational signal that we experience as a whole, which isn’t entirely separate from our experience of our external context (blurry line). What we perceive in the world is viewed through our internal context (if you’re inside that bubble looking out, everything will be tinted blue). This is why we can all react in different ways to the ‘same’ ‘external’ stimuli and why we may act differently in different contexts. All is through the filter of our experience and through relation, after we become old enough to have a symbolic world. This symbolic world is, in some respect verbal but more importantly highly symbolic. Words/language are one important network that forms the scaffolding of our internal experience, and which we can somewhat efficiently use to show others our world.
That ‘sticky’ scaffolding gives words power.
So, RFT is not just a theory of language. It is a theory of symbolism.
‘Anything can become anything’ because it is nearly all symbolic at some level.
Sensation, perception, visual stimuli, auditory stimuli, words, actions, are all a symbolic soup of experience, and your own relational history makes some of those cues more salient than others.
For example, listen to just a second of this music. Close your eyes. Notice the feelings and thoughts.
Now, what you all experienced was the same stimulus, but how it affected you is through relation, in a very deep way.
My experience is not yours, in great part, because of my distinct relational history with this stimulus.
For me, that song is chills, tears in my eyes, the taste of a tequila shot (hey… I was nervous that day), and a visual of walking down the aisle. It will never again be separate from those moments. BECAUSE of the RELATIONS it obtained when I chose it for that defining moment.
For you, maybe it was just squeaky violin music or something pretty. This is RFT. The song had no words and yet it is still symbolic and influenced by what I say. Now, if you meet me, you will have the words above as a scaffolding between our worlds.
As you read them you were likely able, in some part, to experience part of my experience but even still through your relational history. For those of you who know me, the experience of learning this information might have been more intense if I’m close to you or if you experience me as like you. This is predictable based on RFT: a frame of coordination (she is like me) or (I like her) will increase your experience of my description. A frame of distinction (I am not like her) or (this is crap, etc.) will decrease the intensity of the experience (transformation of stimulus functions) evoked by reading my experience.

Cathey (2016)
Thus our experiences are tinted, amplified, and de-amplified by the frames in which we hold ourselves, those we are exposed to, and many other contextual variables that influence our experience.
Isn’t it lovely? We are all connected, through relation. (Imagine: You can totally win 6 degrees to Kevin Bacon now. 😉

Media: www.mangowed.com
Further, your actual perceptual, emotional, behavioral, and verbal experience is predicable based on RFT and the significance or depth of the learning you have related to the the stimuli (REC Model; Hughes, Barnes-Holmes, Vahey, 2012; Barnes-Holmes, Barnes-Holmes, Stewart, & Boles (2010)).
So, let’s switch frames a bit to get ready for clinical/social applications:
Let’s look at the REC Model of some things that could cause us to feel fear or disgust. This is a functional example. It’s not perfect but let’s hope it gets the job done. Look at the items in the REC Model below and note your emotional response.
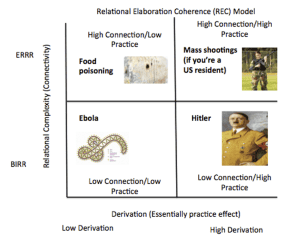
Cathey (2016)
What I’m willing to bet is that even though you likely have some very rich sensory experiences (high connectivity) of food poisoning, unless you’ve had one recently you probably didn’t have much of a response to that stimuli. As a US resident, few of us will have a strong visceral response to Ebola as its not connected to most things in our daily worlds. Few of us will have had direct experience with it.
Now here’s the curious part, what was your response to the gun woman? What was your response to Hitler?
If you had a more intense emotional response to Hitler that is understandable based on REC, but few other theories would predict this or allow for testing of it. We could say that we have “habituated” to gun violence. Or, perhaps we’ve now heard so many derivations of this occurring that we can now control the response to it, as it is sunken into the rich networks of other relations.
Hitler, on the other hand. I’m guessing no one reading this met him. Yet you may have felt a lurch of disgust even stronger than the food poisoning picture.
Without RFT and personal experience with this it is difficult to make sense of your response to Hitler, vs food poisoning, vs. mass shootings, vs. Ebola.
Stay with me here. A low complexity network with high derivation is a bit like all the relations flowing through this single point of symbolic ‘evil’. If he is a single point of relation through which all we know about the Holocaust and those horrors is filtered there is a lot of derivation through repeated understanding but little complexity. For most of us we only have knowledge of these things through history classes, documentaries, etc. This results in a highly derived but not complex network of emotional learning. It lends itself to strong/rigid/somewhat two dimensional responses.
Otherwise it’s a little difficult to explain why we’d have such a strong response to someone none of us have ever met AND yet have a have a much more moderated response to gun violence.
Clinical Behavior Analyst, Methodologist & Trainer
Angela J. Coreil, PhD, is a professor at the University of Louisiana at Lafayette, clinical behavior analyst, and methodologist. Formerly director of an OCD and anxiety IOP/PHP, she integrates behavior analysis, ACT, Interpersonal Behavior Therapy, CBT, and exposure-based treatment. Her work develops practical improvements in behavioral science, and she provides consultation, professional training, workshops, and continuing education across disciplines.
Views expressed are those of Dr. Coreil or the explicitly named author, not the University of Louisiana at Lafayette.
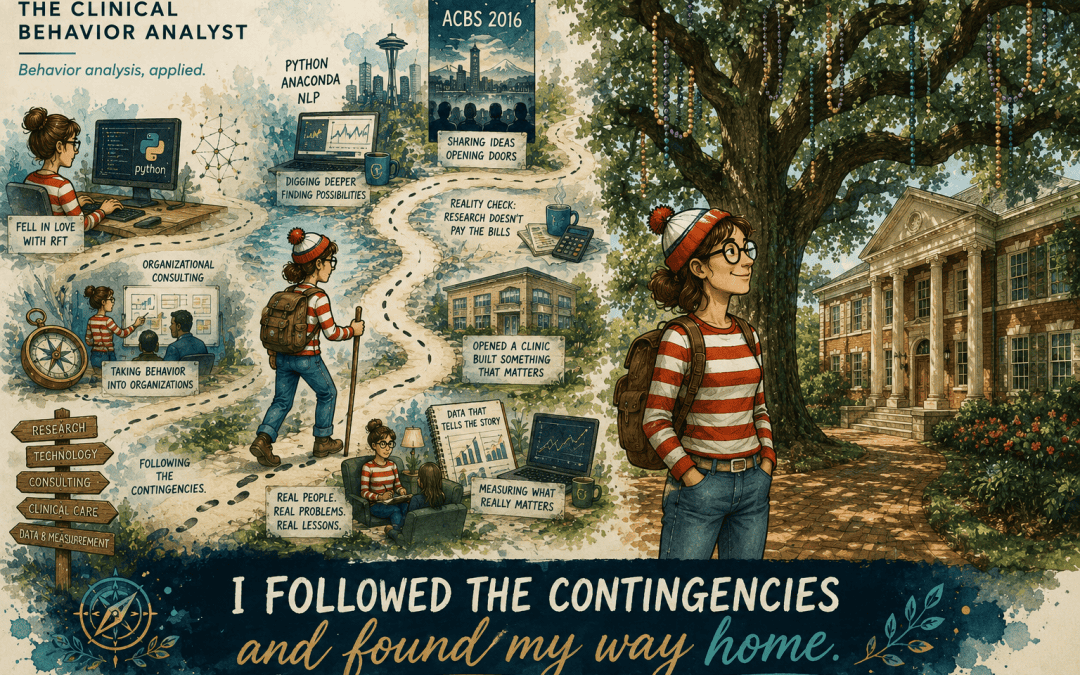
For a while, I stopped writing so much. Life had a lot of turns in store for me.I kept thinking about measurement, language, and understanding complex human behavior in context. Those questions simply moved with me across contexts.
Around 2015, I had already fallen in love with Relational Frame Theory and Clinical Behavior Analysis. RFT gave me a flexible way to bring language, thought, meaning, and symbolic behavior into behavioral analysis without abandoning behavioral principles. It opened a door I had been trying to find for years. And yes, I know – I’d been an ACT clinician forever, but RFT evolved. Once I saw what might be possible, I wanted to know how far it could go.
The research was important, but contingencies had me finding reinforcement outside the lab. The beauty of behavior analysis and human language is that its everywhere. Language changing across settings, relational patterns unfolding over time, and then I learned that clinicians were interested in the technology but bringing it to them wasn’t feasilble at the time. The NSF i-corps taught me Lean Start-up though and I rolled with it. I landed organizational gigs and I bootstrapped ways to run what I wanted to build myself.
What I-Corps changed was my understanding of how scientific advances might become products, services, and tools that people could actually use. It taught me to think about customers, implementation, workflows, and whether an idea could survive outside the conditions in which it was developed.
That mattered. I learned to bootstrap prototypes. For those of you that are unfamilair, here’s an example of a bootstrapped prototype.
A scientific advance can be brilliant and still go nowhere. Someone has to make it usable. (And, as above – eventually someone has to make it not look like a circuit board in a suitcase.) Someone has to understand the environment into which it will be introduced. Someone has to build the bridge between an important finding and getting people to make use of the finding.
I began doing organizational work with medium-sized companies. I worked on problems involving communication, leadership, culture, employee behavior, and the ways verbal networks shape what organizations do. and what people buy. I enjoyed it. Organizations offered a remarkably rich setting for thinking about relational responding, rule-governed behavior, and behavior across complex systems.
The work also showed me how much behavioral science could contribute outside traditional clinical and academic settings. But organizational contracts move slowwwwwly.
A company may spend months discussing a project, revising the scope, securing approval, and moving through procurement before anyone gets paid. That timeline may be manageable for an established consulting firm. It is much harder for a doctoral student raising a toddler.
At the same time, I was receiving invitations into exciting academic conversations, including opportunities to spend time around research programs I admired. I was deeply interested in that work.
Interest, however, does not pay the bills.
I had a child to raise, a doctorate to complete, and a life that required income on a schedule more reliable than organizational consulting or emerging research collaborations could offer.
So, I followed the contingencies.
Clinical work paid more reliably, and I knew I how to a run specialized Intensive Outpatient (IOP) and Partial Hospitalization (PHP) units from previous work. In 2018, I opened the Better Living Center for Behavioral Health.
I built an intensive behavioral health center from the ground up. Seeing my first clients involved renting their therapy room for an hour while paying for 1.5 hours of drop-off care. But, I am scrappy. I hired and trained clinicians, supervised treatment, developed programs, managed crises, built documentation systems, negotiated with insurers, handled compliance, fixed operational problems, and learned every part of running a clinical organization. The result was an 18 room higher-level treatment facility specialized for treatment of severe OCD and anxiety disorders.
The clinic was a master class in so much. I had treated complex clients. I had trained clinicians but as the CEO of a treatment facility everything was mine to solve. Someday, over a drink, you can ask me about poop-ma-gedon. (Hint: It wasn’t an exposure exercise.)
But in the mix of this work, again – the same themes ate at me. Clients did not arrive as clean constructs. They did not separate themselves into neatly bounded diagnoses, treatment protocols, or theoretical models. They arrived with overlapping histories, medical conditions, family systems, complex verbal repertoires, changing environments, practical constraints, and problems that behaved differently across contexts.
The harder the case, the more obvious it became that no single treatment model could anticipate all of the complexity in front of us. Evidence-based treatments remained essential. The work was learning how to apply them intelligently to the individual.
That required following behavioral principles, observing closely, adapting carefully, and asking better questions.
What is happening? Under what conditions? What changed?
What could a clinician realistically collect while still providing care?
Running a clinic changed how I understand science. It showed me how reimbursement shapes treatment. It showed me how organizational contingencies shape clinician behavior. It showed me how documentation requirements alter what gets observed and what gets ignored.
It also showed me how often useful information gets lost. Rich clinical observations become checkboxes. Repeated reports become total scores. Language becomes a diagnosis. Complex behavior gets flattened into categories that fit billing systems, electronic records, or research conventions.
The clinic made it impossible for me to treat measurement as a neutral activity. Measurement always occurs inside a system. The system determines what gets collected, what gets rewarded, what gets retained, and what gets discarded.
It also made clear the kinds of issues that occur when solutions meet clinical reality. A sophisticated tool that clinicians cannot use is not useful. A measure that takes too long will not be completed. A dashboard no one understands will be ignored. A theoretically elegant system that does not fit the workflow will disappear. Those lessons now sit at the center of how I think about research.
There is a recognizable academic path: graduate school, post-doc, faculty position, publications, lab, promotion.
I’ve never been one to follow the beaten path. My path moved through research, technology, organizational consulting, entrepreneurship, intensive clinical care, business ownership, supervision, insurance systems, and the daily work of keeping an organization alive.
The years of finding my potential forever home – they were worth it all. They were where I learned what happens when theory meets reimbursement, staffing, liability, time pressure, and the lives of actual clients. They were where I learned that implementation is not an afterthought. It is part of the science.
I came back to academia understanding how to build my work in ways that can survive and thrive within systems. And, now, I’m home and happy to be writing again.
Clinical Behavior Analyst, Methodologist & Trainer
Angela J. Coreil, PhD, is a professor at the University of Louisiana at Lafayette, clinical behavior analyst, and methodologist. Formerly director of an OCD and anxiety IOP/PHP, she integrates behavior analysis, ACT, Interpersonal Behavior Therapy, CBT, and exposure-based treatment. Her work develops practical improvements in behavioral science, and she provides consultation, professional training, workshops, and continuing education across disciplines.
Views expressed are those of Dr. Coreil or the explicitly named author, not the University of Louisiana at Lafayette.

By Angela Coreil, PhD, LP, BCBA
One of the things that first drew me to Relational Frame Theory (RFT) was that it finally provided a behavior-analytic framework capable of addressing the complexity of human language. Rather than treating thoughts and language as something outside the domain of behavior analysis, RFT offered a principled way to integrate verbal behavior into behavioral analysis while remaining grounded in basic behavioral principles. It felt like finding a missing piece.
As exciting as that realization was, it immediately led to another question:
How do we actually measure complex verbal behavior outside of the laboratory?
Around 2015, that question sent me down a rabbit hole that consumed much of my free time. I began teaching myself the emerging world of natural language processing. I dug through Python libraries, Anaconda environments, early machine learning tools, and resources that would eventually evolve into platforms like Hugging Face. I wasn’t approaching these technologies as a computer scientist. I was trying to answer a behavioral question:
Could these emerging computational methods help us measure verbal behavior in ways that were more consistent with contextual behavioral science?
In 2016, I presented some of these early ideas at the Association for Contextual Behavioral Science (ACBS) Research-Based Practice Special Interest Group in Seattle. The excitement surrounding the possibilities eventually grew into this manuscript, co-authored with the wonderful Olga Berkout and Karen Kate Kellum.
The paper argues that Contextual Behavioral Science has an opportunity to advance measurement by treating language itself as behavior rather than simply as evidence for latent psychological constructs. Building on Relational Frame Theory, we proposed that emerging Natural Language Processing (NLP) technologies could begin measuring increasingly complex verbal behavior across applied and clinical settings while maintaining greater theoretical consistency with functional contextualism.
Rather than viewing written and spoken language merely as indicators of underlying mental states, we suggested analyzing language directly as observable behavior. We outlined how computational linguistics, ecological momentary assessment, mobile technologies, and behavioral signal processing might eventually be integrated to examine verbal behavior as it unfolds across time, contexts, and social interactions. At the time, many of these ideas were speculative. Today, many have become technically feasible.
The manuscript also sought to address one of the longstanding challenges facing Relational Frame Theory: translating decades of elegant basic research into tools that clinicians and applied researchers could actually use. We discussed integrating contemporary RFT models, including the Multi-Dimensional Multi-Level (MDML) framework, with modern computational methods to visualize and quantify increasingly complex relational networks as they emerge in everyday language.
Looking back, many of the ideas I continue to pursue – including treating self-report as verbal behavior rather than latent variables, integrating ecological momentary assessment with physiological and language data, preserving behavioral observations rather than collapsing them into composite constructs, and developing scalable behavioral measurement systems – can be traced back to the questions first explored in this paper. In many ways, this manuscript marked the beginning of my effort to build a more integrated science of human behavior.
Berkout, O. V., Cathey (Coreil), A. J., & Kellum, K. K. (2019). Scaling-up assessment from a contextual behavioral science perspective: Potential uses of technology for analysis of unstructured text data. Journal of Contextual Behavioral Science, 12, 216–224. https://doi.org/10.1016/j.jcbs.2018.06.007
Related Works:
Berkout, O. V., Cathey (Coreil), A. J., & Berkout, D. V. (2020). Inflexitext: A program assessing psychological inflexibility in unstructured verbal data. Journal of Contextual Behavioral Science, 18, 92–98. https://doi.org/10.1016/j.jcbs.2020.09.002
Cathey (Coreil), A. J., Holman, G., Villatte, M., Zettle, R., Canare, D., & Swails, J. (2016, June). Adapting research to the clinical environment: Computer-aided verbal behavior analysis (CAVBA). Association for Contextual Behavioral Science Annual Conference, Seattle, WA.
Cathey (Coreil), A. J., Vilardaga, R., & Zettle, R. D. (2016, June). Using ecological momentary assessment to examine the impact of self-regulation choice on affect. Association for Contextual Behavioral Science Annual Conference, Seattle, WA.
Cathey (Coreil), A. J., Zettle, R. D., & Swails, J. (2016, April). Computer-aided verbal behavior analysis (CAVBA): Evidence for the feasibility of detecting framing behavior with natural language processing. Wichita State University Research Roundup, Wichita, KS.
Clinical Behavior Analyst, Methodologist & Trainer
Angela J. Coreil, PhD, is a professor at the University of Louisiana at Lafayette, clinical behavior analyst, and methodologist. Formerly director of an OCD and anxiety IOP/PHP, she integrates behavior analysis, ACT, Interpersonal Behavior Therapy, CBT, and exposure-based treatment. Her work develops practical improvements in behavioral science, and she provides consultation, professional training, workshops, and continuing education across disciplines.
Views expressed are those of Dr. Coreil or the explicitly named author, not the University of Louisiana at Lafayette.

By Angela Coreil, PhD, LP, BCBA
One of the most surprising things I’ve learned after years of clinical practice is that becoming a better therapist wasn’t about learning another therapy. It was about learning the common language underneath them.
If you practice long enough, you’ll eventually encounter clients for whom there simply are no relevant randomized controlled trials. That’s not because our evidence-based treatments are inadequate. It’s because no randomized controlled trial could ever capture the complexity of the clients we actually see in practice.
The moment you begin combining diagnoses, developmental histories, medical conditions, family systems, cultures, learning histories, and environments, the number of possible combinations becomes enormous. No treatment manual could reasonably anticipate all of them. As clinicians, we’re then faced with a challenge. We still want to provide evidence-based care, but we also have to adapt that care to fit the individual sitting in front of us.
That means supervision, reading across literatures, and learning how to translate what “works” from one therapeutic language into another.
Over the years, I’ve trained extensively in Acceptance and Commitment Therapy (ACT), Cognitive Behavioral Therapy (CBT), Functional Analytic Psychotherapy (FAP), Exposure and Response Prevention (ERP), and Prolonged Exposure (PE). I’ve trained less deeply in Compassion-Focused Therapy, Schema Therapy, and even spent some time learning psychodynamic approaches.
On the surface, these therapies often appear very different. They use different terminology, different conceptual models, different intervention strategies, and sometimes different assumptions about why people change.
Yet when you sit in a room with a client – what happens isn’t actually “ACT”, “CBT”, or any therapy name. At a very important level, all that ever occurs in those rooms is two people ‘behaving.’ Whether you’re doing exposure therapy, cognitive restructuring, metaphors, etc…. it is all words (vocal verbal behavior), body movements, and the like. Some of you are going to have your hackles up already.
Calm those feathers down! I’m not discounting all or certain therapies. We simply forget that we can describe behavior and record BEHAVIOR without inferring that it means something else. That doesn’t mean every therapy is “really behavior analysis”, nor does it mean that theoretical differences don’t matter. Rather, behavioral principles provide a common scientific language that allows us to understand, compare, and translate across treatment approaches.
In the most difficult cases I’ve treated, I rarely found myself abandoning evidence-based treatments. Instead, I found myself applying behavioral principles ideographically. The treatment remained evidence-based. The application became individualized. For me, that has been one of the greatest practical values of learning clinical behavior analysis.
Researchers face a different—but related—challenge. Psychotherapy research continues to evolve. Process-based therapy, for example, represents an important attempt to move beyond comparing therapy brands and toward understanding mechanisms of change. I think that movement is asking many of the right questions. At the same time, much of our research, and the process-based work, still depend on composite constructs. Those constructs become the variables that organize entire research programs. As our theories evolve, so do the constructs and the measures designed to assess them.
There is another way to think about this. Instead of moving toward increasingly complex constructs, we can also move toward increasingly behavioral measurement. What do I mean by that? Take a construct like anxiety sensitivity. Most anxiety researchers recognize that anxiety sensitivity has long been conceptualized as a combination of physiological reactivity and beliefs or expectancies about what those bodily sensations mean.
Put simply, it is something like:
“My body reacts strongly, and that reaction means something bad is going to happen.”
I’m intentionally simplifying here—the anxiety sensitivity literature is much richer than that—but the point illustrates an important measurement issue. (Don’t flood with me with comments on how this is inaccurate. It’s an example). Instead of measuring only the composite construct, we could separately measure the components. We could directly measure physiological responding. (Yes, I know logistics, sensitivity, and specificity… again, example.)
We could separately measure the individual’s verbal behavior about those experiences. When I say verbal behavior, I don’t necessarily mean only what someone ‘says’ in therapy. It includes the language we collect through questionnaires, ecological momentary assessment, interviews, natural language samples, and other forms of measurement. Rather than immediately treating those responses as indicators of an underlying construct, we can first view them simply as behavior worthy of analysis in its own right.
That shift changes the assumptions we make about our data. More importantly, it creates opportunities.
First, your research becomes more durable. If future researchers redefine anxiety sensitivity, develop a better measure, or propose a different construct altogether, your original behavioral observations remain useful. You still have the physiological data. You still have the verbal behavior. Those observations can be reorganized under future theories without losing the original information.
Second, keeping the raw behavioral observations allows us to ask questions that today’s theories may not even anticipate. As our methods improve – particularly in areas like ecological momentary assessment, passive sensing, and natural language processing – we may discover behavioral patterns that were hidden when everything was reduced to a single total score.
I suspect this will become increasingly important over the next few decades.
Clinical behavior analysis has become valuable to me because it gives me a common language for both clinical practice and research. As a clinician, it has helped me understand how to adapt evidence-based treatments without abandoning the evidence. As a researcher, it has changed how I think about measurement and the kinds of data I want to preserve for future analyses.
If those ideas interest you, follow along. Many of the future blogs on this site will explore how clinical behavior analysis can help us think more clearly about therapy, assessment, measurement, and the science of behavior.
Clinical Behavior Analyst, Methodologist & Trainer
Angela J. Coreil, PhD, is a professor at the University of Louisiana at Lafayette, clinical behavior analyst, and methodologist. Formerly director of an OCD and anxiety IOP/PHP, she integrates behavior analysis, ACT, Interpersonal Behavior Therapy, CBT, and exposure-based treatment. Her work develops practical improvements in behavioral science, and she provides consultation, professional training, workshops, and continuing education across disciplines.
Views expressed are those of Dr. Coreil or the explicitly named author, not the University of Louisiana at Lafayette.