
Select Page
Computational Functional Analysis: Extending functional analysis into the digital age

Computational Functional Analysis: Extending functional analysis into the digital age

A brief update to a talk originally presented at the Association for Contextual Behavioral Science (ACBS) World Conference in Seattle, Washington, June 2016. 

Nearly ten years ago, I had the opportunity to present an idea that felt, at the time, almost impossibly ambitious. The project was called Computer-aided Verbal Behavior Analysis (CAVBA). The presentation asked a deceptively simple question:

“Could technology help clinicians conduct richer, more contextual functional analyses?”

Looking back, many of the technologies discussed in that presentation have become ordinary. Smartphones continuously collect behavioral data. Wearable devices monitor physiology. Ecological Momentary Assessment (EMA) has become increasingly common. Natural language processing has advanced at a pace few of us anticipated.

What still feels unfinished is not the technology. It’s situating the data in a conceptual and technical framework that ‘works’ for others to use it. This was an issue from the beginning. I used data visualizations like the ACT Matrix to help people make sense of a lot of data easily. I could have used heat maps, graphs, or any number of visual representations – but what’s important is that people have to be able to easily make sense of the data.

The problem was never a lack of data

At the time, clinicians were already struggling with assessment. Clients rarely completed questionnaires consistently. Measures were often collected too infrequently to guide treatment. Clinical practice rarely resembled the carefully controlled conditions of randomized clinical trials. Comorbidity was the rule rather than the exception.

From a contextual behavioral perspective, this created a mismatch. Functional analysis asks us to understand behavior in context. Our assessment methods were increasingly removing behavior from the very contexts in which it occurred.

Functional analysis deserved better tools

The original project was named Computer-aided Verbal Behavior Analysis (CAVBA), but the software itself was never the primary contribution. The larger idea was what I would now call Computational Functional Analysis.

What is Computational Functional Analysis?

Computational Functional Analysis is a behavior-analytic framework for organizing multiple streams of behavioral data, including verbal behavior, direct observation, ecological momentary assessment, physiological measures, and environmental context, into a form that aids the clinician’s functional analysis. Computational methods assist by integrating and prioritizing observations within an interbehavioral field, while functional interpretation remains the responsibility of the clinician.

Those observations might include:

  • verbal behavior during therapy;
  • verbal behavior outside therapy;
  • Ecological Momentary Assessment (EMA);
  • physiological measures;
  • movement and environmental context;
  • clinician observations;
  • behavioral outcomes across time.

The purpose is not to reduce these observations to a single score. Nor is it to infer hidden psychological constructs from increasingly sophisticated statistical models.

Instead, the goal is to help clinicians organize observations behaviorally – to identify meaningful relationships, generate functional hypotheses, and prioritize intervention. Technology assists. The clinician still conducts the functional analysis.

Why multiple behavioral streams, over time, matter

One aspect of the original presentation that has become even more important to my thinking is the recognition that behavior occurs simultaneously across many interacting systems.

A client’s physiology may change. Their languaging will shift. Their overt behavior may change in different ways across the contexts in their daily lives. And, that’s really the point, isn’t it? We don’t do therapy to improve the client’s behavior IN THERAPY. We do therapy so the client’s life improves. We can’t know if our work is having an impact in the way we want without measuring more of the client’s interaction with their actual life. Generalization is a fairly basic behavioral principle, but we seem to have traded it in on the idea that if we change the hypothetical “depression” or “anxiety” driving the person’s behavior, it will change their behavior in other contexts.

Organizing behavior as an interbehavioral field

Over time, my thinking has become increasingly influenced by Kantor’s interbehavioral field construction. Because the objective isn’t just to collect masses of data, anyone can tell you that will just be a mess. We want to collect data that is most likely to drive behavior and prioritize our streams based on behavioral principles.

To be theoretically consistent, you’re going to look at your data only with the base level assumptions. A questionnaire item endorsed is a moment in time, decontextualized verbal report. Verbal behavior over time is a signal, not a sign. Physiological measures are likely to be organized as setting factors, not some ground-level truth prioritized above other things.

Reading the slides from my 2016 talks nearly a decade later, I’m struck by how much of the technology and the world have caught up. In 2016, I would get two different kinds of responses. “We looked into this in the 1980’s and it’s just word counts,” or on the other end, “Is the Terminator going to be reading my email?” (Those are, in fact, both actual responses I received to CAVBA. Now, people are quite acquainted with natural language processing. LLM’s now masquerade nearly successfully as humans. The difficult problems today are no longer technical or perceptual. The logistics that hog-tied me in 2016 no longer apply.

Now, it’s just the conceptual and technical refinement. In many ways, CAVBA was never simply a software project. It was an early attempt to imagine what functional analysis might become when clinicians could finally observe behavior across the complexity of everyday life.

I think that conversation is only just beginning.

 

Angela Coreil, PhD, BCBA

Angela Coreil, PhD, BCBA

Clinical Behavior Analyst, Methodologist & Trainer

Angela J. Coreil, PhD, is a professor at the University of Louisiana at Lafayette, clinical behavior analyst, and methodologist. Formerly director of an OCD and anxiety IOP/PHP, she integrates behavior analysis, ACT, Interpersonal Behavior Therapy, CBT, and exposure-based treatment. Her work develops practical improvements in behavioral science, and she provides consultation, professional training, workshops, and continuing education across disciplines.

Views expressed are those of Dr. Coreil or the explicitly named author, not the University of Louisiana at Lafayette.
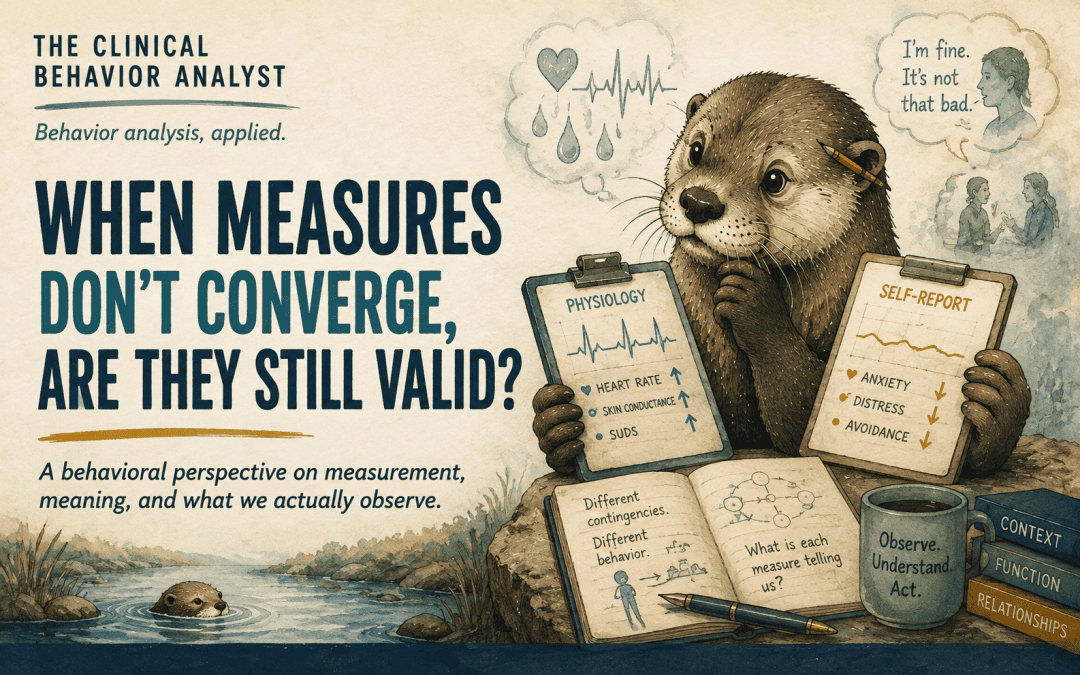
When measures don’t converge, are they still valid?

When measures don’t converge, are they still valid?

One of the most influential concepts in psychological measurement is convergent validity.

The idea seems straightforward. If several different measures are supposed to assess the same phenomenon, we would expect them to agree. If they do, we often become more confident that we’ve measured something “real.”

That sounds sensible.

Until you stop and ask a simple question:

What exactly have we observed?

Imagine someone with a snake phobia.

As they approach the snake, their heart rate increases. Their hands begin to sweat. At the same time, they continue walking toward the snake because their therapist is encouraging them and they are committed to treatment. If you ask them what they’re thinking, they tell you they are imagining themselves somewhere else entirely.

Three different response systems.

Three different patterns of behavior.

Which one tells us how afraid they “really” are?

From a behavioral perspective, that question is actually the wrong place to begin.

Each of those responses is behavior occurring under somewhat different environmental influences. The physiological response may reflect years of learning in which snakes became associated with danger. Walking toward the snake may be controlled by social reinforcement. The person’s verbal report may indicate rule-governed behavior, or not.

Why would we expect these behaviors to match perfectly?

What happens if, instead of asking “which one tells us how ‘afraid’ they really are?”, we ask “which one is going to be most tied to the change we’d like to drive?” We need to stop assuming “afraid” is some ‘thing’ we can accurately detect. 

Staying close to what we actually observed

This is one of the places where I think psychology sometimes moves too quickly away from its observations. Suppose someone completes a questionnaire designed to measure anxiety.

What did we actually observe?

We observed that a person endorsed a series of verbal statements in response to a particular set of prompts, under a particular set of circumstances.

That’s the observation.

Everything beyond that requires another inference.

If that questionnaire correlates highly with another questionnaire asking similar questions, what have we learned?

We have learned that people tend to respond similarly to similar verbal prompts.

That is an interesting and important finding.

But it is not, by itself, proof that an underlying psychological entity called “anxiety” or “fear” has been discovered.

The data demonstrate consistency in responding. Whether that consistency reflects an internal construct, a learned repertoire, recurring environmental contingencies, stable patterns of relational responding, characteristics of the measurement situation, or some combination of these remains a separate scientific question.

Those are different claims.

And they require different evidence.

Behavior analysis takes a more conservative position.

Behavior is treated as behavior.

Not as a sign pointing toward some hidden thing that must exist behind it.

That doesn’t mean internal events are ignored. It means we begin with what we can actually observe and then ask what variables are influencing those observations. When different measurements disagree, the first question isn’t, “Which one is right?”

Instead, it’s, “What environmental variables might be influencing each of these different behaviors?”

Sometimes disagreement between measures isn’t ‘measurement error’. Sometimes it is exactly what we should expect.

A person’s physiology, overt behavior, and verbal behavior are all influenced by overlapping—but not identical—histories and current contingencies.

Understanding why they diverge may teach us far more than forcing them into agreement.

Angela Coreil, PhD, BCBA

Angela Coreil, PhD, BCBA

Clinical Behavior Analyst, Methodologist & Trainer

Angela J. Coreil, PhD, is a professor at the University of Louisiana at Lafayette, clinical behavior analyst, and methodologist. Formerly director of an OCD and anxiety IOP/PHP, she integrates behavior analysis, ACT, Interpersonal Behavior Therapy, CBT, and exposure-based treatment. Her work develops practical improvements in behavioral science, and she provides consultation, professional training, workshops, and continuing education across disciplines.

Views expressed are those of Dr. Coreil or the explicitly named author, not the University of Louisiana at Lafayette.

Functional Relational Analysis: RFT infused functional analysis

Functional Relational Analysis: RFT infused functional analysis

Editor’s Note (2026): This article was originally published on AngelaCathey.com in 2016. It is reproduced here with only minor grammatical edits for readability. Some resources and terminology have evolved since its original publication, but the conceptual discussion is presented largely as it appeared at that time.

Here’s an outline for today’s post:

1. Functional Analysis (FA) our most powerful and under-utilized tool.
2. What RFT can offer to FA.
3. General guidelines for bringing RFT-FA into the room via integration with the 5 Rules of FAP.
4. A few groups of relations described functionally
5. What RFT-guided FA could do for our ability to assess the effectiveness of functionally oriented treatments (e.g., FAP).
RFT has a lot to offer for the applicability, precision, and utility of Functional Analysis.

Functional Analysis is one of our most powerful therapeutic frameworks in behaviorism (underlying most of our orientations), yet it has fallen out of use in the clinical environment.

Why? Because:

1) We are generally not in the client’s environment to see the variables controlling their behavior.
2) People are exceedingly bad at understanding/describing the variables that control their own behavior (see above on seeing everything through your own relational history and Measurement: Why we get no R.E.S.P.E.C.T., which explains how CBS has tried to deal with issues of measurement in relation to behavior).
3.) And, in the therapy hour, what you can do with FA is often to teach the client how to recognize (and hopefully influence) their own behavior or contexts, outside the therapy environment. Then you hope for the best.

So, let’s consider FA and what RFT-informed Functional Analysis has to offer clinicians:

First, by gaining experiential knowledge of RFT/REC, we get a much better picture of what variables may be controlling the client’s behavior, in the room and in their lives.

Second, we get a much better picture of how to intervene effectively by being able to test our hypotheses (often per session) by altering the variables in the room (in the present moment) and paying attention to the client’s response, our experience, and other contextual variables.

Thus, with RFT/REC we can go a long way to restoring our ability to use functional analysis during the therapeutic hour. (Not to mention getting more of the warm fuzzy feeling you get when you realize you’re doing something that’s ‘working’ for the client.)

So, let’s talk about how we can begin to use RFT in Functional Analysis. I’ll present some general guidelines and then discuss the how and why of these.

You’ll also notice that this is going to map right onto the “5 Rules” of Functional Analytic Psychotherapy. (Addition, 2026 note – I am speaking about the models of Functional Analytic Psychotherapy that were deeply behavioral and not the “Awareness, Courage, and Love” ACL model here.)

This is purposeful, as in my experience: 1) FAP is already one of the models that purposely trains you to bring FA into the present moment and look at behavior functionally, rather than topographically, and all we’re really doing here is adding knowledge of how the properties of symbolic relating also get tied into all the other ‘behaviors’ you see.

Note: This isn’t meant to substitute for or be better than learning RFT in other forms. If you want a full, more advanced understanding of RFT, I would recommend starting with Villatte, Villatte, and Hayes’ Mastering the Clinical Conversation or Matt Villatte’s online course on RFT through Practice Ground. Much of what I say here is an entry point to what these resources and others (such as Hayes’ Rule-governed Behavior) may teach you.

1. First, and above all else, listen to the client’s experience. (Rule 1: Watch for CRB1s AND watch for the general pattern of behavior (verbally and ‘non-verbally ‘) around important relations.)

2. Look for rule-governed behavior and rules. (If you’re in a stuck spot and feel like you’re bumping your head against the wall, it’s highly likely that either you and/or the client are responding to a ‘rule’.) This is Rule 1 again, but rule-governed behavior is such a big factor in the breakdown of communication I feel it stands repeating.

3. Understand what the HOW of the behavior tells you. (Again, Rule 1 in FAP but extended to understanding, using RFT, the function and properties of the symbolic relations that show up in the room.)

4. Start altering the context in the room, in the moment, with your hypotheses and noting the client’s HOW of response. (This is Rule 2, Evoke, from the FAP model, except evoke is also extended to using RFT to evoke verbal relations and understand the client’s response.)

5. Relate (functionally). (This is Rule 3, Reinforce, from the FAP model, except when you bring RFT into the mix, you begin to see how many more ways you can affect the client’s relating to you, themselves, the world, their pain, etc right there in the moment. This may sound a bit foreign, but I almost promise you that you’re already doing some form of it. If you’re an ACT clinician and the client is fused. then you get them to defuse. Congrats! You just moved a relation! Except RFT has far more to offer than defusion. Some of which I’ll describe below.)

6. Note your impact on relations as well as other behavior (Rule 4, Notice your impact except extended to noticing your impact on relations and their properties as well as other behavior).

7. Provide functional interpretations (Rule 5, in FAP) except that I would say that ‘functional’ may also need to be seen from an RFT perspective. Sometimes it’s helpful to provide direct feedback about the relations you perceive, but we also know that humans like simplicity a bit too much. Careful with providing interpretations that may easily be turned into rules (and rule-based insensitivity), so tread lightly and experientially here.

Included in this, but discussed less, is an assumption of general knowledge regarding Functional Analysis and Functional Assessment. For readers who want a review of this, start here: Iwata & Dozier, 2008; Gareth Holman’s Intro to FA on Practice Ground; and for mapping out your effect for research (or warm fuzzies), begin with Koerner and Holman’s 2014 Single-case designs in clinical practice.

It’s good to have a general awareness of how the character of the behavior (e.g., approach/repeat may indicate presence of reinforcing qualities) may indicate relations. Then in the FA you learn the problematic relation only through noticing what moves the relation in a more adaptive direction (functionally determined).

How do you know what’s adaptive? I like Villatte, Villatte, and Hayes’ Mastering the Clinical Conversation overall framework.

That is, the overall goals of treatment are:

1. Helping the client develop flexible context sensitivity and functional coherence (read awareness when it’s adaptive and an overall system of relating that ‘works’ for the client).

The overall means of treatment are:

1. Transforming symbolic functions by altering context (read influencing relations and their properties by any of your symbolic behavior in the room with the client, etc.)

So, in doing a Functional Relational Analysis, we’re doing an in-the-moment analysis to increase adaptive relating as defined by Villatte, Villatte, and Hayes in the manner in which we influence relating with the 5 Rules in FAP (you following me?)

So, now about the business of recognizing relations that can be influenced in your RFT-FA. First, let’s begin by making things a bit simpler: some relations that frequently come up and affect treatment in the moment.

1. Rule-governed behavior – consider this a kind of fusion that, in whatever form, usually results in an inability to contact important contingencies at hand.

Example(s): “Jimmy is always anxious.” vs “Jimmy is anxious.” vs. “Jimmy sometimes gets anxious.” Inherent in these statements is a rule. Though you’d need ideographic context, they may likely indicate different levels of fusion with the rule. The intensity/rigidity and lack of noticing other contingencies may give you a good idea about how fused the speaker is to the rule and how unaware they may be when Jimmy acts in ways that are non-anxious (see later post on discrimination/stigma/violence towards others). Keep in mind that almost any kind of relation can be rule-ified into inflexibility over time, repetition, etc.

2. How to influence it: Defusion, context changes of many sorts (emotion, experientially walking through the contingencies that allow the person to note what was previously missed, etc.

3. How to assess your impact: Is the person now loosening in their behavior guided by the rule? Is their language around the rule more flexible?

2. Influencing awareness towards whole or parts – here I’m talking about several relations in combination functionally. We often use distinction framing (this but not that), combination (this and this), opposition (this is the opposite of that) to bring more awareness to the parts and pieces. 

Examples(s): Hierarchicals and moving towards seeing the self or experience as a part of the continuing experience. “I am this feeling, this moment” versus “I am more than my experience.”

How to influence it: Mindfulness, either noticing continuity, wholeness, or otherwise noticing detail.

How to assess your impact: Do they seem (verbally or otherwise) more aware of the direction needed to note important contingencies? Other relations can also be added in, but let’s focus on these for now.

What can elements of an RFT allow us to fine-grain and repeated attempts to change relating of several types each session?

We can aim for more or less flexibility, more or less awareness of certain contingencies, and more adaptive stories about the “self” and its experience. This can allow several dimensions for FA beyond what is normally present.

Add the REC Model, and you can evaluate behavior based on its complexity and derivation (allowing you to see whether you need to increase the variety and complexity of learning experiences to make it stable and adaptive).

Further elaborating on this kind of workup could help us more effectively assess some of the benefits of functionally oriented treatments.

Essentially, mapping out change in other relations would add further assess change.

For example, we know that one of the mechanisms responsible for the effectiveness of FAP is likely to be contingent reinforcement (see Kanter, Landes, Busch, Rusch, Brown, Baruch, and Holman 2006 Effect of contingent reinforcement) and that systems can be derived for measuring change based on this functional target (see Callaghan 2001 FIAT Functional Ideographic Assessment Template).

With RFT, everything can be parsed relationally in some respect (every treatment, nearly every behavior, diagnosis, etc.). This, in combination with other FA relations (e.g., reinforcement), can allow us to examine change across therapies, diagnoses, contexts, etc. Further, noticing the change in relation in verbal behavior gives us many more opportunities for altering and assessing our impact each session.

If you’re thinking that assessment and coding of verbal relations would take years, wait for the posts on Natural Language Processing, Machine Learning, and sensor-based experience sampling.

References

Iwata, B. A., & Dozier, C. L. (2008). Clinical application of functional analysis methodology. Behavior Analysis in Practice, 1(1), 3–9.

Callaghan, G. M. (2001). Functional Ideographic Assessment Template (FIAT) System. Reno, NV: Context Press.

Hayes, S. C. (Ed.). (1989). Rule-Governed Behavior: Cognition, Contingencies, and Instructional Control. New York: Plenum Press.

Kanter, J. W., Landes, S. J., Busch, A. M., Rusch, L. C., Brown, K. R., Baruch, D. E., & Holman, G. I. (2006). The effect of contingent reinforcement on target variables in outpatient psychotherapy for depression: An investigation of Functional Analytic Psychotherapy. Journal of Applied Behavior Analysis, 39(4), 463–467. https://doi.org/10.1901/jaba.2006.21-06

Koerner, K., & Holman, G. I. (2014). Single-case designs in clinical practice. In The Wiley Handbook of Contextual Behavioral Science

Villatte, M., Villatte, J. L., & Hayes, S. C. (2016). Mastering the Clinical Conversation: Language as Intervention. New York, NY: Guilford Press.

Psychotherapy’s Taxonomy Problem

Psychotherapy’s Taxonomy Problem

Psychotherapy’s Taxonomy Problem

Why We Keep Arguing About Mythical Animals Instead of Studying Behavior

Imagine walking into a county fair where the grand prize is about to be awarded for Best Animal. One contestant is an elephant with zebra legs, butterfly wings, peacock feathers, and octopus tentacles. The next is a giraffe with the body of a bear, tiger paws, and the tail of a fish.The judges are having an intense argument.

Which creature is more authentic? Which one has the better anatomy? Which one deserves the blue ribbon for Effective Treatment?

No one stops to ask a more fundamental question.

When did we stop studying animals and start arguing about mythical ones?

Sometimes I wonder whether psychotherapy has wandered into the same county fair.

Every generation of researchers tries to build a better way of understanding human suffering. That’s exactly what science should do. New theories propose new mechanisms. New measures. New therapeutic languages. New ways of organizing behavior.

Over time, though, something subtle happens.

We stop treating those theories as useful maps and begin treating them as though they were different species inhabiting nature.

ACT becomes one animal.

CBT becomes another.

Psychodynamic therapy, DBT, Process-Based Therapy, Unified Protocols—they each develop their own anatomy, their own vocabulary, and their own criteria for what healthy functioning looks like.

Then the debates begin.

One of the most common arguments is that comparing therapies like ACT and CBT is like comparing apples and oranges.

I think we’ve accepted the wrong conclusion.

Apples and oranges are remarkably easy to compare.

We compare them by properties they both possess: acidity, water content, sugar, fiber, weight, shelf life.

What we don’t do is ask whether the orange became a better apple.

Yet that’s surprisingly close to how psychotherapy research often operates.

Each theory develops its own mechanisms.

Its own process measures.

Its own language.

Its own explanations.

Then we ask whether each therapy became a better version of itself.

The more our theories evolve, the stranger the animals become.

New mechanisms are added.

Old concepts are borrowed.

Measures are refined.

Constructs multiply.

Eventually we’re no longer comparing elephants and giraffes.

We’re comparing beautifully assembled mythical creatures built from decades of accumulated assumptions.

Then we race them.

We hand out blue ribbons.

And we argue endlessly about which mythical animal won.

I don’t think this is because psychotherapy research is failing.

I think it’s because our theories have become more sophisticated than the way we measure them.

Karl Popper reminded scientists that observations are never interpreted in isolation. Every scientific test rests on a network of assumptions connecting theory to observation. The challenge is not pretending those assumptions don’t exist; it’s remembering that they’re there.

Perhaps psychotherapy has become so successful at building increasingly sophisticated theories that we’ve started mistaking the theories for the thing they were created to explain.

The thing we were trying to understand was never ACT.

Or CBT.

Or any other named therapy.

It was human behavior.

Maybe the next step in psychotherapy isn’t inventing another mythical animal.

Maybe it’s learning how to measure the behavioral dimensions that all of them have in common.

Because mature sciences don’t advance by becoming more loyal to their taxonomies.

They advance by discovering ways to build knowledge across them.

Angela Coreil, PhD, BCBA

Angela Coreil, PhD, BCBA

Clinical Behavior Analyst, Methodologist & Trainer

Angela J. Coreil, PhD, is a professor at the University of Louisiana at Lafayette, clinical behavior analyst, and methodologist. Formerly director of an OCD and anxiety IOP/PHP, she integrates behavior analysis, ACT, Interpersonal Behavior Therapy, CBT, and exposure-based treatment. Her work develops practical improvements in behavioral science, and she provides consultation, professional training, workshops, and continuing education across disciplines.

Views expressed are those of Dr. Coreil or the explicitly named author, not the University of Louisiana at Lafayette.

What is ‘clinically relevant behavior’: Sign or sample

What is ‘clinically relevant behavior’: Sign or sample

By, Angela Coreil, PhD, LP, BCBA
As discussed by Ollendick et al. (2004), abnormal and clinically-relevant behavior can be viewed as either a “sample” or as a “sign.” To what extent does this difference, in turn, make a difference in the assumed temporal and situational consistency of such behavior?

Whether you view abnormal and clinically-relevant behavior as a “sample” or a “sign” makes a significant difference in whether you consider such behavior to be consistent over time and in various situations. If a behavior is seen as only a “sample” of a person’s behavior then there is no expectation that this behavior will be consistent over time or in different situations. When behavior is only said to be only a “sample” the implication is that you expect variation in the behavior. If the behavior is thought of as a “sign”, however, the implication is that the behavior is only an indication of an underlying trait or pathology which implies that the behavior should be more constant through time and situations. From this view as long as the underlying pathology, trait, etc. is present then behavioral “signs” of the underlying construct should also be present. In the relation to psychological problems this “sign” conceptualization, however, is most often a circular or reifying argument. A “sign” behavior indicates a “disorder” when a “disorder” only indicates a collection of symptoms. This conceptualization provides no particular “cause” for the behavior other than itself. This conceptualization is an artifact of using the methods of physicians to understand physical disease to understand human behavior.

The understanding of behavior as a “sample” vs a “sign” also impacts how problem behavior is conceptualized and in turn how assessment is conducted. If the behavior is only a “sample” of a person’s behavior at a certain time in a certain situation than an assessment of the person’s behavior in other situations is likely to be important. If the behavior is a “sign” then assessment over one time period in one situation is more acceptable because the behavior is assumed to be stable as long the “disorder” is constant. Assessment of “sample” behavior may also involve a less predetermined route than assessment of “sign” behavior. As behavior seen as a “sample” implies that there may be a wide variety of other problem behaviors that may exist with the target behavior. Thus, assessment may include any route of questioning, observing etc. that helps the clinician learn about all problem behavior and any possible relationships between the environment and problem behaviors. Because the behavior is expected to vary by situation, factors related to the situation may more likely be considered part of the conceptualization of the problem and should be assessed. If behavior is conceptualized as an “sign”, however, the behavior is related to internal factors and assessment is more likely to focus on assessing for other problem behaviors that are understood to cluster to indicate the underlying pathology. Assessment of environmental/situational factors is also less important if the behavior is understood to indicate pathology as the person’s behavior should continue to indicate the pathology across situations. In other words, assessment from a “sample” behavior perspective is more likely to be all-inclusive in assessing what other behaviors are present and what factors may be causing the problem behavior. Assessment from behavior as a “sign” perspective is more likely to be limiting in the sense that the clinician begins by looking specifically for behaviors that indicate a disorder and is more likely to ignore situational factors in the behavior and understand the “disorder” indicated the cause of the problem behavior.


Angela Coreil, PhD, BCBA

Angela Coreil, PhD, BCBA

Clinical Behavior Analyst, Methodologist & Trainer

Angela J. Coreil, PhD, is a professor at the University of Louisiana at Lafayette, clinical behavior analyst, and methodologist. Formerly director of an OCD and anxiety IOP/PHP, she integrates behavior analysis, ACT, Interpersonal Behavior Therapy, CBT, and exposure-based treatment. Her work develops practical improvements in behavioral science, and she provides consultation, professional training, workshops, and continuing education across disciplines.

Views expressed are those of Dr. Coreil or the explicitly named author, not the University of Louisiana at Lafayette.

Measurement: Why we get no R.E.S.P.E.C.T.

Measurement: Why we get no R.E.S.P.E.C.T.

“MEASUREMENT: WHY WE GET NO R.E.S.P.E.C.T.”
Editor’s Note (2026): This article was originally published on AngelaCathey.com in 2016. It is reproduced here with only minor grammatical edits for readability. Some resources and terminology have evolved since its original publication, but the conceptual discussion is presented largely as it appeared at that time.

Psychologists, therapists, and researchers in mental health:

How many times have you been at a party and told someone you’re a psychologist only to hear, “So, you can read my mind?”… or, “Can you analyze my dreams for me?”

Why does this happen?

The public has no idea what we do. At best, we’re often perceived as paid friends or mistaken for psychiatrists.

And, maybe we can live with this but it isn’t just the public. 

The National Institute of Mental Health (NIMH) is a major funder of our research… or it used to be. The recent move towards Research Domain Criteria Initiative (RDoC) for NIH funding means that obtaining a grant for an RCT from the NIH requires that you heavily integrate investigation of possible biological factors in your study to obtain funding. This has occurred despite the fact that most of the field (psychology) agrees that biological components aren’t driving contributors in most maladaptive behavior. In fact, years of searching for specific biological profiles for diagnoses has turned up little useful information. Still we’re on the search for the right blood test, fMRI, EEG, or otherwise, that will diagnose people, why?

Because – it makes what we do ‘real’ for them.  

So, what are the consequences of this search for ‘real’… thing-y-ness in mental health?

If you’re a clinician, not seeking research funding, you may not immediately contact what this means for you. So, here’s my take: If you’re using Beckian-CBT or even ACT, you’re probably fine. We’ve already got loads of RCTs to show these ‘work’. This means you can probably count on insurance companies giving you less of a hassle for treatment reimbursement.

If, by chance, you are using anything else that has had few RCTs you might have problems eventually. If we can’t get said treatment determined an ‘Empirically Supported Treatment’ through the current standard of massive and repeated RCTs. (Eh hem.. FAP. One of the most behavior analytic in-the-moment treatments struggles with RCTs because they are based on our most effective tool (functional analysis). Functional analysis is ideographic and doesn’t easily conform to RCT methodology. This is part of the reason for the build out of the ACL model… a need to standardize functional analysis. )

Well, I’m sorry but if we have to alter a treatment that is driven by a tool we all respect then our overall measurement/methodology strategy sucks. In fact, psychoanalysts were saying this about RCTs from the beginning but when we were in a foot race with them it was a little hard to hear the truth in it.

So, what I’m getting at here is several levels of pervasive problems related to our field… but thankfully, they’re related. 

Some of you may not like what I say here. I fully expect to get a few angry emails (Save it, prove me wrong with data.).

So, here’s my analysis of what’s causing these problems:

In a word: Measurement!

In a few words: Reifying rigidity! Constructs! and lack of integration!

Okay, so I’m probably at a level of geekery here that few will understand. So, this is what I’m talking about.

So, why am I picking on constructs?

We all use constructs. We have to so we can get through the day. Clinicians can’t walk around explaining to each other from the ground-up what “psychological flexibility”, “response flexibility”, “borderline”, “depression”, or anything means. That’s impractical but we do need to continually contact the effect of this on our methods and the perception of the world. Then we need to choose our level of analysis appropriately.

If we assess only at the level of constructs without awareness of the consequences then we’re essentially shooting ourselves in the foot. 

We’ve measured mostly in constructs because measuring real behavior was HARD. We know that behavior and report of behavior vary by context (e.g., mood state bias, retrospective report bias, rule-governed behavior, and the list goes on…) so we’ve tried to standardize the heck out of measures. We’ve measured mid-level concepts that attempt to represent whole clusters of supposedly important relationships. Then, because the public wouldn’t understand this… we have to integrate symptom inventories to give it some ‘realness’. It’s a chain reaction.

When we measure constructs we need them to hold still and mean something so we apply psychometric rules that assume thing-y-ness and stability to these airy clouds of invention. Then we make it ‘real’ with symptom inventories that use diagnostic labels that the public gets, but which we know have poor as hell diagnostic reliability (not surprising since they are essentially Chinese menu style creations. Congrats! pick 5 out of 7 and ooo. la. la. you’re depressed.)

Before you get ‘depressed’ reading this let’s take a ‘beginner’s mind’ to assessment (as Todd Kashdan suggests) and look at how we can fix these problems. 

Let’s build from the ground up. 

Let’s understand our assumptions and what works. Let’s start by measuring behavior, in context, across contexts. 

Contextual Behavioral Science has been moving towards this for years. Some of our brightest minds in theory, philosophy of science, treatment, and methodology have been telling us to go there for years (e.g., Roger Vilardaga, Kelly Koerner, Todd Kashdan, Kelly Wilson, and many others.)

For the interested, here are a few citations:

Wilson, Hayes, Gregg, & Zettle (2001). Psychopathology and Psychotherapy (Chapter in Big Purple).

Wilson (2001). Some notes on constructs: Types and validation from a contextual behavioral perspective

Hughes, Barnes-Holmes, & Vahey (2012). Holding onto our functional roots while exploring new intellectual islands: A voyage through implicit cognition research ***The Relational Elaboration Coherence model and RFT based assessment***

Vilardaga, Bricker, & McDonell (2014). The promise of mobile technologies and single case study designs for the study of individuals in their natural environments.

Iwata, DeLeon, & Roscoe (2013) The FAST. Functional Analysis Screening Tool

Hurl, Wrightman, Hayes, & Virues-Ortega (2016). Does a pre-intervention functional assessment increase intervention effectiveness? A meta-analysis of within-subject interrupted time-series studies. (**Spoiler alert: Yes, it does.**)

Since you probably didn’t click on any of those:

We have better methods now. We can use technology to assess behavior (across contexts), to intervene, and to rapidly and cheaply assess behavior. Take a moment: Look at your iPhone… That thing ‘knows’ more about you than your best friend or your spouse.

So, why aren’t we using these methods? Well, I hear you. Most of us weren’t taught to create Apps in grad school, to deal with data flow that exceeds the capability of SPSS, or to understand the intersection between technology and confidentiality. For most of us, even though we let Target (who lost tons of credit card numbers. yikes!), Apple, Best Buy, Netflix, and many others track our every move we’re not utilizing this technology well in the behavioral sciences.

Essentially: Who has time to learn entire new areas of science (App design, UX, Data Science, Python, R, etc.)  in order to have better and cheaper assessment? 

It’s not that people aren’t trying. I certainly heard a lot of interest in Ecological Momentary Assessment (EMA), Ecological Momentary Intervention (EMI), Relational Frame Theory, and links from basic to applied at the CBS conference this year but these things aren’t exactly user- friendly straight out the ‘box.’

Notably: There have been some valiant efforts to create systems of assessment and data tracking that ‘work’ for clinicians and researchers.

See:

Learn2ACT an integrated system of Acceptance and Commitment Therapy (ACT) driven mobile client-client centered data collection and intervention. It tracks and logs data for multiple clients and displays it for clinicians. Big props to Ellen & Bart for taking this on from programming to testing. Release of this product is currently scheduled for some time in Fall (so show them some love and for doing all this work for us)!

Other systems in development include Matrix (ACT-driven) Apps out of Mike Levin and Beniji Schoendorff’s groups. Roger Vilardarga and Jonathan Bricker and others also have out Apps that are a bit more target specific (e.g., ACT driven for psychosis, smoking cessation, etc.) – (Forward me links to anything else that is evidence-based or getting that way and I’ll consider listing them too.)

The process of gaining an evidence base for this technology (Mental Health Smart Phone Apps: Review and evidence-based recommendations for the future development), while mastering all this tech, and paying attention to user experience (UX) AND getting people aware of these technologies is a difficult one. So, as a community I think we need to support efforts to develop technologies that make it easier for clinicians and researchers to use functional contextual behavioral assessment.

I’m working on an integrated functional analysis driven assessment platform and I need your feedback. 

My concept is a bit different but also includes EMA/EMI, as this is our best CBS consistent context sensitive assessment effort thus far.

Stay with me here:

I propose that we also go from basic research and theory and build a system that integrates what we know to the best of our ability. One that is functional analysis driven, contextually-sensitive, rapid, and user-friendly. Then we make this available such that we can funnel meta data (read de-identified behavioral data on relations) to basic and applied researchers from clinicians. After all, those RCTs aren’t even touching how to treat complicated multi-problem clients.  

Such a system would involve:

  1. Contextualized behavioral assessment (EMA/EMI and passive assessment of biometrics. Hey, we’re not going to bowl the NIH and RDOC over all at once.)
  2. Assessment of verbal/symbolic related behavior (aka… integrating what we know from RFT into understanding contextualized functional analysis driven assessment.

Note: You won’t have to go read Big Purple to use this system. We’re planning to present relations in pretty visual analytics that even clients can make sense of. We’d like to make explaining relationships (between verbal behavior and verbal behavior or verbal behavior and EMA/EMI passive behavioral data ) functional. Wouldn’t it be nice if you could such demonstrate your outcomes in forms that show you make ‘real’ change in the lives of your clients?

See previous post on RFT: Relational Frame Theory (RFT)- What’s the big deal? And, Hayes & Berens (2004) Why Relational Frame Theory alters the relationship between basic and applied behavioral psychology for why RFT is important to this. If, your mind just squealed… “but relating and frames are just constructs!” See future post on empirical logic and the difference between reifying constructs and properties.

Essentially, we need to add in RFT because we know that verbal/symbolic relations can more powerfully influence behavior in the moment than the actual contingencies. Additionally, integrating RFT allows us to step back and forth from behavior, to intervention, to level of appropriate measurement across diagnoses and therapy orientation – so maximum flexibility and applicability.

I understand that many of you may be thinking at the point… so, are we talking assessing the content of language? Word counts? 

Well, no and yes… we do look at the verbal content but we can look at functional relations indicated between verbal relating and verbal relating, or between this and other behavioral measures. I’ll save that for another post.

For now, here’s some ground work within CBS that supports the use of attempting to assess verbal/symbolic relating through language:

Atkins & Styles (2016). Measuring self and rules in what people say: Exploring whether self-discrimination predicts long-term well-being (ACBS membership needed to view).

Collins, Chawla…Marlatt (2009). Language-based measures of mindfulness: Initial validity and utility

If you’re interested in learning more about clinical behavior analysis, RFT, and advanced measurement methods – let us know in the comments below! We also have some online, on-demand training events on a variety of topics that may interest you.

Angela Coreil, PhD, BCBA

Angela Coreil, PhD, BCBA

Clinical Behavior Analyst, Methodologist & Trainer

Angela J. Coreil, PhD, is a professor at the University of Louisiana at Lafayette, clinical behavior analyst, and methodologist. Formerly director of an OCD and anxiety IOP/PHP, she integrates behavior analysis, ACT, Interpersonal Behavior Therapy, CBT, and exposure-based treatment. Her work develops practical improvements in behavioral science, and she provides consultation, professional training, workshops, and continuing education across disciplines.

Views expressed are those of Dr. Coreil or the explicitly named author, not the University of Louisiana at Lafayette.

Pin It on Pinterest